The Complete Omega-3 Guide: EPA, DHA, Choosing a Supplement, and Synergies
1. What Omega-3 Actually Is
Omega-3 fatty acids are essential polyunsaturated fats, meaning the body cannot make them and they must come from diet or supplements. The two forms with the strongest evidence base are EPA (eicosapentaenoic acid) and DHA (docosahexaenoic acid), found mainly in fatty fish and algae. A third form, ALA (alpha-linolenic acid), comes from plant sources like flaxseed and walnuts, but the body converts only a small fraction of it into EPA and an even smaller fraction into DHA[1].
EPA and DHA are structural components of cell membranes throughout the body, are especially concentrated in the retina and brain, and serve as precursors to signalling molecules involved in resolving inflammation. This combination of roles is why omega-3 research spans cardiovascular health, brain function, eye health, and inflammatory conditions.
2. A Deep Dive Into Omega-3's Studied Effects
Cardiovascular Health — The Most Researched Area
Omega-3 has one of the largest cardiovascular trial literatures of any supplement, and the results are genuinely mixed rather than uniformly positive. Large trials such as VITAL and ASCEND, using moderate doses (roughly 1 g/day) in general or diabetic populations, found little to no reduction in major cardiovascular events. In contrast, the REDUCE-IT trial, using a high-dose purified EPA prescription formulation (4 g/day) in people already on statins with elevated triglycerides, found a substantial reduction in cardiovascular events — a result that has driven prescription-strength omega-3 therapy for that specific population. The takeaway is that dose, formulation, and the population studied all matter enormously, and general-purpose supplements at typical over-the-counter doses should not be expected to replicate REDUCE-IT-level results.
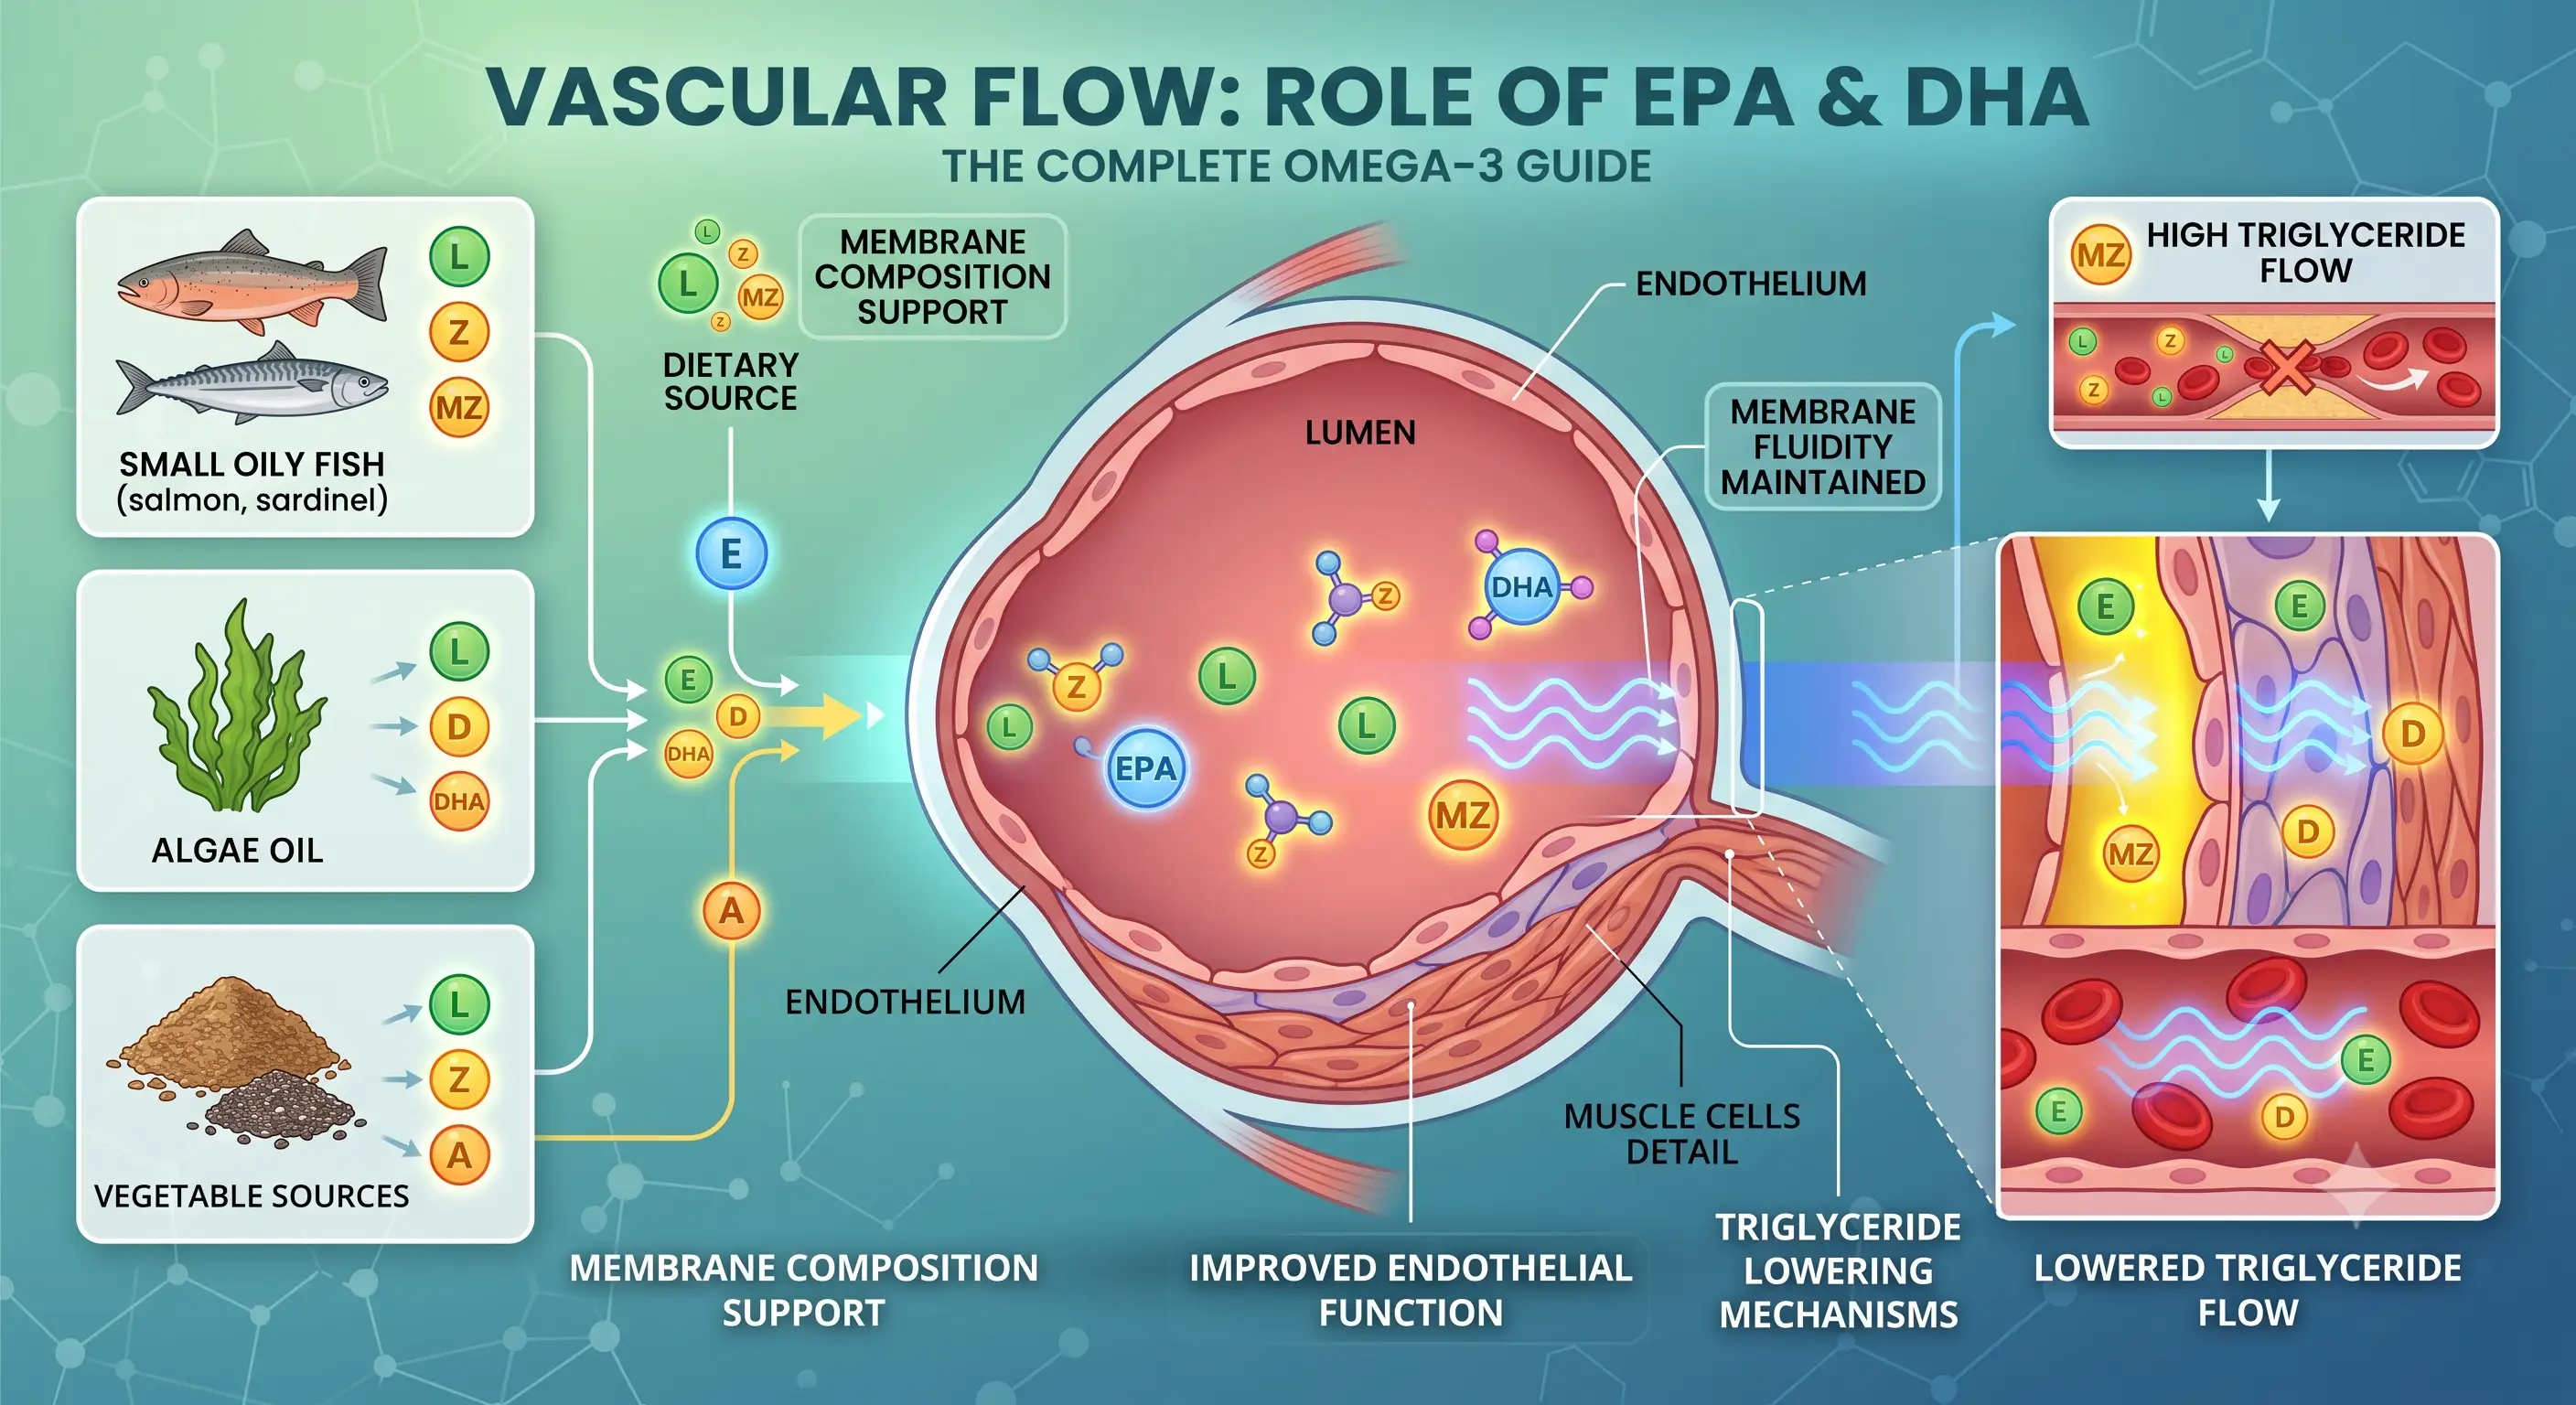
Omega-3 reliably and meaningfully lowers triglycerides at doses of 2–4 g/day — this is one of its most consistent and clinically established effects, which is why prescription formulations are FDA-approved specifically for very high triglycerides.
Brain Health and Cognitive Function
DHA is a major structural fat in brain tissue, and observational studies link higher omega-3 intake to better cognitive outcomes with age. Interventional trial evidence for slowing cognitive decline or treating dementia is weaker and more mixed, and omega-3 should not be presented as a proven cognitive treatment — the observational and mechanistic case is stronger than the interventional trial case.
Eye Health
DHA is highly concentrated in retinal photoreceptors. Omega-3 was one component of the AREDS2 formulation studied for age-related macular degeneration, though in that specific large trial adding omega-3 did not provide additional benefit beyond the core AREDS2 formula. It remains relevant for general eye health and dry eye, where some trials show modest symptom improvement.
Mood and Depression
Meta-analyses of omega-3, particularly EPA-predominant formulations, as an adjunct to standard depression treatment show modest positive effects in some populations. It is studied as an adjunct to, not a replacement for, standard depression care.
Inflammatory and Joint Conditions
Omega-3's role as a precursor to specialized pro-resolving mediators gives it a plausible anti-inflammatory mechanism, and some trials in rheumatoid arthritis show modest reductions in joint tenderness and reduced NSAID use. Evidence in osteoarthritis is weaker.
What the Evidence Does and Doesn't Show
| Use | Strength of evidence | Notes |
|---|---|---|
| Lowering high triglycerides | Well established | 2–4 g/day; prescription forms FDA-approved |
| Cardiovascular events, high-risk + high-dose EPA | Strong in specific trial (REDUCE-IT) | Not generalizable to low-dose OTC use |
| General cardiovascular prevention, moderate dose | Limited (VITAL, ASCEND) | Little benefit in general populations |
| Depression (adjunct, EPA-predominant) | Modest positive | Adjunct only, not a replacement |
| Rheumatoid arthritis symptoms | Modest positive | Reduced tenderness, less NSAID use |
| Cognitive decline prevention | Weak/mixed interventional evidence | Stronger observational link |
3. Shop Smart: How to Choose the Right Omega-3
Step 1: Check EPA + DHA Content, Not Just "Fish Oil 1000mg"
A 1000 mg fish oil capsule often contains only 300 mg of combined EPA and DHA, with the rest being other fats. Read the supplement facts panel for the actual EPA and DHA amounts, not the total oil weight.
Step 2: Form — rTG vs. Ethyl Ester vs. Triglyceride
| Form | Notes |
|---|---|
| Natural triglyceride (TG) | Found in whole fish and standard fish oil; well absorbed |
| Ethyl ester (EE) | Common in concentrated formulas; somewhat lower absorption, especially without food |
| Re-esterified triglyceride (rTG) | Concentrated form converted back to triglyceride structure; generally best absorption among concentrated forms, at a higher price |
| Algae oil | Vegan source of DHA (and sometimes EPA); the reliable option for those avoiding fish |
Step 3: Check for Oxidation and Third-Party Testing
Fish oil oxidizes over time, degrading quality and producing the unpleasant "fishy burp" — a strong fishy smell from the bottle itself (not just the capsules) is a sign of oxidation. Look for third-party testing (IFOS, USP, or NSF) for purity, potency, and low oxidation (TOTOX) values.
4. Everyday Habits: Getting Omega-3 From Food
- Fatty fish: Salmon, mackerel, sardines, herring, and anchovies are the richest dietary sources of EPA and DHA. Two servings per week is a commonly cited general target.
- Algae-based foods: The original source of omega-3 in the marine food chain; algae oil is the vegan alternative to fish oil.
- ALA sources: Flaxseed, chia seeds, walnuts, and canola oil — healthy fats, but not a reliable route to meaningful EPA/DHA levels due to poor conversion.
- Favor smaller fish: Sardines, anchovies, and mackerel accumulate less mercury than large predatory species like swordfish or king mackerel.
- Balance omega-6 intake: Typical Western diets are heavy in omega-6 from vegetable oils; this doesn't require eliminating omega-6, but ensuring adequate omega-3 intake alongside it is the more relevant framing than chasing a specific ratio.
5. The Perfect Match: Synergies and Incompatibilities
✅ Combinations That Work Well Together
- Vitamin E: Fish oil supplements commonly include a small amount of vitamin E as an antioxidant to protect the oil itself from oxidation during storage.
- CoQ10: Both are studied in cardiovascular contexts and are commonly paired in heart-health formulas, though they act through different mechanisms.
- Lutein: Both concentrate in the retina; sometimes combined in eye-health formulas alongside DHA's own retinal role.
- Vitamin D: Both are fat-soluble and often taken together with a meal for absorption; frequently studied together in cardiovascular and immune research, though effects are generally assessed independently.
❌ Separate These / Use With Caution
- Blood thinners (warfarin, aspirin, clopidogrel): Omega-3 has a mild antiplatelet effect; at high doses it can add to bleeding risk. Discuss with a physician, especially before surgery.
- High-dose combined use: Stacking multiple omega-3 sources (fish oil plus krill oil plus algae oil) can unintentionally push total EPA/DHA intake above what's needed or studied for safety at very high combined doses.
6. Dosage, Timing, and Safety
Practical Approach
- General health: 250–500 mg combined EPA + DHA daily is a commonly cited general target, roughly matching what two servings of fatty fish per week provides.
- Triglyceride management: 2–4 g/day EPA + DHA, generally used under medical guidance given this is in prescription-strength territory.
- Timing: Take with a meal containing some fat, which improves absorption and reduces fishy aftertaste.
- Storage: Keep refrigerated after opening to slow oxidation, especially in warmer climates.
Common Side Effects
Fishy aftertaste or burps are the most common complaint, usually reduced by taking with food, choosing enteric-coated capsules, or freezing capsules before taking them. Mild digestive upset and loose stools can occur at higher doses.
7. Frequently Asked Questions
Q. Do I need rTG, or is regular fish oil fine?
A. Regular fish oil taken with a fatty meal is fine for most people. rTG may absorb somewhat better, but consistency, a decent EPA + DHA dose, and freshness matter considerably more than the form.
Q. Can I just eat flaxseed instead?
A. Flaxseed is a healthy food, but conversion of ALA to EPA is limited and to DHA is minimal. If you avoid fish, algae oil is the more reliable route to DHA.
Q. Why do my capsules taste fishy?
A. Usually either oxidation or taking them on an empty stomach. Take with food, keep the bottle refrigerated, and replace it if the smell is strong — oxidized oil is not worth taking.
Q. Will fish oil prevent a heart attack?
A. That is not something a general supplement has been shown to do. Eating fish regularly is well supported as part of a heart-healthy pattern; specific high-dose prescription therapy has a defined role in selected patients, decided by a physician.
Q. Should I worry about mercury?
A. Quality supplements are molecularly distilled and third-party tested, and mercury is generally not detectable. For dietary fish, favour smaller species and follow local advisories, especially in pregnancy.
8. Conclusion and Precautions
Omega-3, in the form of EPA and DHA, has one of the deepest and most nuanced evidence bases of any supplement — genuinely strong for triglyceride management and for high-risk cardiovascular patients on high-dose prescription therapy, more modest for general cardiovascular prevention, and reasonably supportive across brain, eye, mood, and inflammatory contexts without being a proven treatment in any of them. The honest summary is that eating fatty fish regularly remains the best-supported approach for most people, with supplementation as a reasonable and low-risk way to close the gap, provided the product is fresh, adequately dosed, and third-party tested.
⚠️ Precautions: The FDA has not evaluated omega-3 supplements for the treatment of any medical condition beyond specific FDA-approved prescription formulations for very high triglycerides, and this article is not medical advice. Discuss use with a physician if you take blood thinners, are scheduled for surgery, or are considering high-dose (above 3 g/day) therapy. Choose third-party tested products to minimize mercury and oxidation exposure. Consult a healthcare professional before use during pregnancy or breastfeeding, or if you have a bleeding disorder or cardiac arrhythmia.
9. Sources and References
- National Institutes of Health (NIH), ODS — Omega-3 Fatty Acids Fact Sheet for Health Professionals
https://ods.od.nih.gov/factsheets/Omega3FattyAcids-HealthProfessional/ - American Heart Association (AHA) — Fish and Omega-3 Fatty Acids
https://www.heart.org - Mayo Clinic — Fish oil
https://www.mayoclinic.org - Harvard T.H. Chan School of Public Health, The Nutrition Source — Omega-3 Fatty Acids
https://www.hsph.harvard.edu - Cleveland Clinic — Omega-3 Fatty Acids
https://my.clevelandclinic.org - National Center for Complementary and Integrative Health (NCCIH) — Omega-3 Supplements
https://www.nccih.nih.gov